
Need a Reliable Peptide Supplier? Click HERE!!!SponsoredVisit ↗
GHRP-6 and BAC Water Mix

GHRP-6 Reconstitution Calculator

Enter the amount you want to measure. The vial buttons will highlight which vial strengths create cleaner syringe-unit measurements.

What amount do you need?

Type the target amount, then choose mg or mcg. Example: 2mg or 500mcg.

Work the dose out from body weight

Syringe size:
Possible vial strengths:
Best Match Good Match Usable Harder to Measure

Example GHRP-6 Titration Schedule

ItemDetails
Dose100–300 mcg per injection
Frequency2–3× per day, fasted
Cycle8–16 weeks on / 4–8 off
SignatureStrongest hunger induction of all GHRPs

The founding GHRP (Bowers 1984). Saturation dose is ~1 mcg/kg (~100 mcg); above it, cortisol and prolactin rise instead of more GH. Daily low-dose protocols need the weekly 5-on/2-off rhythm because continuous daily use measurably desensitizes the GH response.

Possible vial strengths:

What Is It?

GHRP-6

Older GH secretagogue with appetite signaling.

Bacteriostatic Water

Sterile water containing a bacteriostatic preservative, commonly used when preparing multi-use research vials.

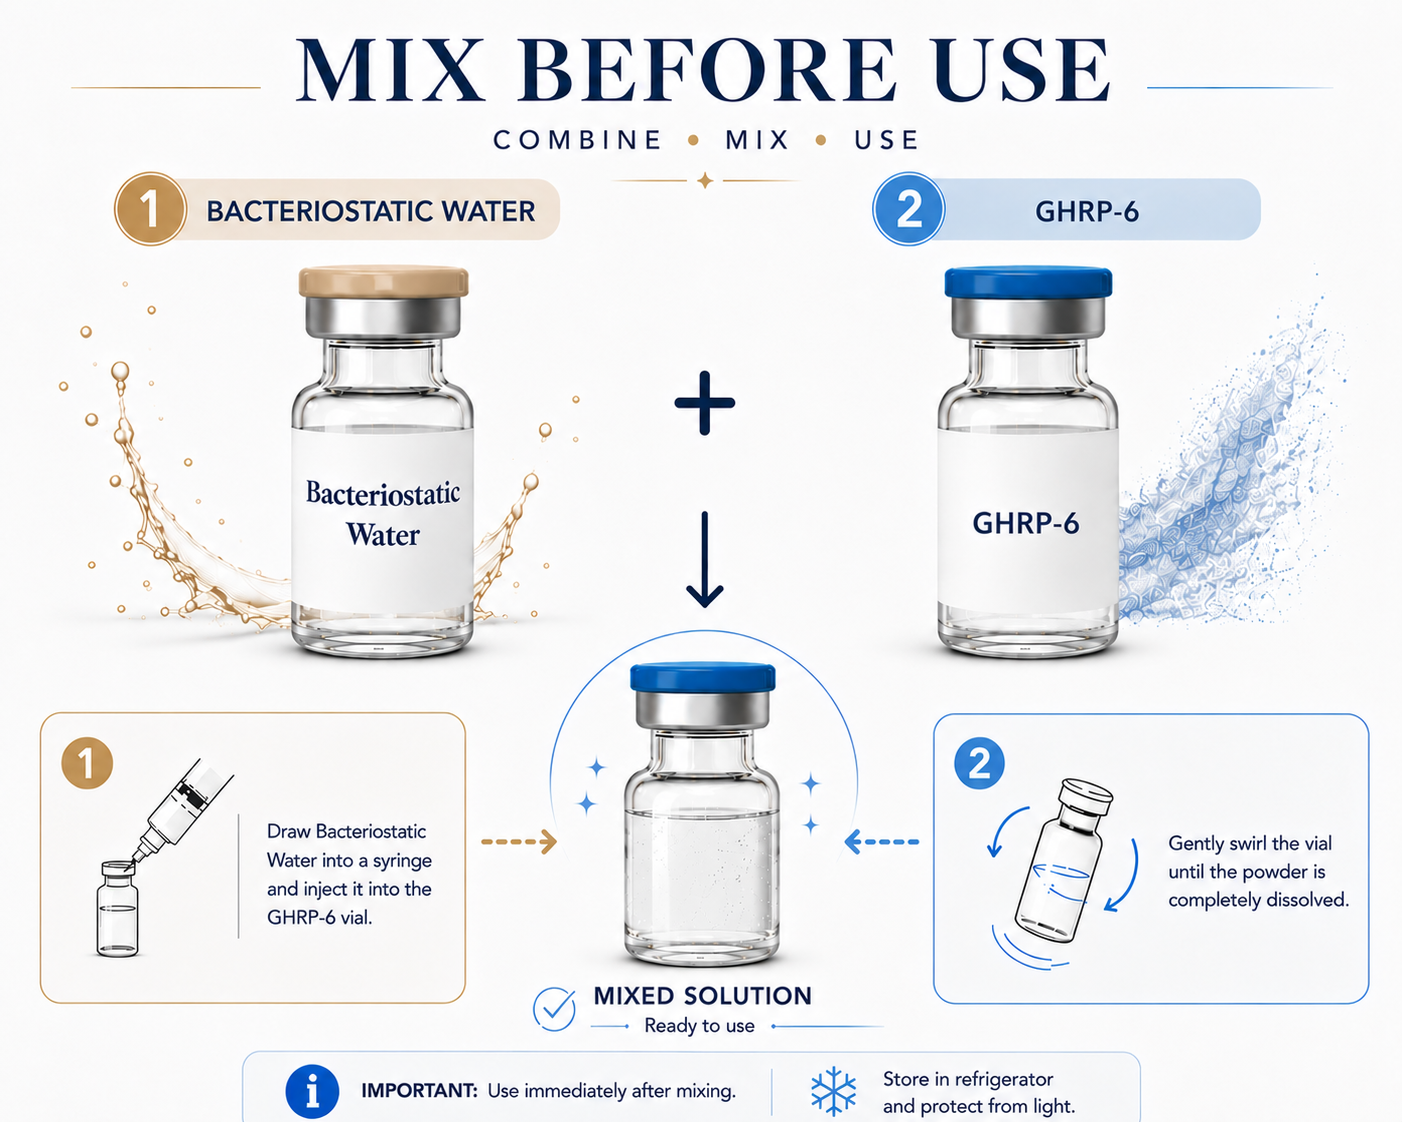
How To Mix GHRP-6

1
Clean

Use alcohol swabs to clean the tops of both vials.

2
Draw BAC Water

Draw the selected amount of bacteriostatic water.

3
Inject Slowly

Add the liquid slowly down the side of the vial.

4
Swirl Gently

Do not shake. Swirl gently until dissolved.

5
Store Properly

Store as directed and protect from heat and light.

Best Practices & Common Mistakes

Best Practices

  • Use sterile technique.
  • Protect from light and heat.
  • Store refrigerated when appropriate.
  • Use clean syringe-unit math before measuring.

Common Mistakes

  • Confusing milligrams with milliliters.
  • Choosing an option with awkward decimal units.
  • Using too little liquid for very small measurements.
  • Shaking the vial aggressively.

GHRP-6 Storage & Handling

Lyophilized Powder: −20°C (−4°F) for long-term storage (up to 24 months). Refrigeration 2–8°C (36–46°F) for short-term use (up to ~3 months). Original sealed vial in the freezer is safest.
Reconstituted Solution: 2–8°C (36–46°F), use within ~7–14 days. Keep sealed, avoid light, and do not repeat freeze-thaw cycles.

Frequently Asked Questions

GHRP-6 is a synthetic hexapeptide and the original growth hormone–releasing peptide, first made in the 1980s. It binds the ghrelin receptor (GHS-R1a) in the pituitary and hypothalamus, prompting your own pituitary to release pulses of growth hormone — it is not a steroid and contains no hormone itself. Among the common GHRPs it's the least selective and the one most defined by a single trait: it makes you intensely hungry. It's a research compound, not an approved medicine.
GHRP-6 is dosed in micrograms — a commonly cited "saturation" dose is about 100 mcg (roughly 1 mcg per kg of body weight), given subcutaneously two to three times a day on an empty stomach. Going much above that doesn't raise GH proportionally; it mainly pushes cortisol and prolactin higher. Its half-life is short, so doses are spread through the day. These are research-reference figures, not an approved schedule, and whether it suits you at all is a clinical question.
Add bacteriostatic water down the side of the dry vial and swirl gently — don't shake. For example, a 5 mg vial + 2.5 mL of water gives 2 mg/mL (2,000 mcg/mL); a 100 mcg dose is then 0.05 mL, which is 5 units on a U-100 insulin syringe. Match the calculator above to your actual vial size (5 mg and 10 mg are common) and target dose. Because doses are tiny micrograms, draw carefully — a single mis-measured unit is a meaningful percentage of the dose.
Yes — intense hunger is GHRP-6's defining feature, typically hitting 15–30 minutes after an injection. It's the strongest appetite stimulant of any GH peptide because it closely mimics ghrelin's signaling in the brain's hunger centers, and it isn't caused by low blood sugar. That makes GHRP-6 a poor fit for fat-loss goals and the reason researchers instead study it for the opposite problem — cachexia, wasting, or appetite loss. If minimal hunger is what you want, ipamorelin is the cleaner end of this family.
There's no human evidence that GHRP-6 causes cancer; the real, documented caution is the one shared by anything that raises GH/IGF-1 — that higher IGF-1 could theoretically feed an existing tumor, which is why GH-raising compounds are avoided in people with active cancer, not evidence that GHRP-6 starts cancer. Commonly reported effects are the strong hunger, mild water retention, and transient flushing or tingling; cortisol and prolactin can rise at higher doses. GHRP-6 is not FDA-approved for any use and is banned by WADA in sport. Store the dry vial cold and out of light; once reconstituted, keep it refrigerated and use within a few weeks.
Practical takeaway: If your goal involves weight management, metabolic health, recovery, physical performance, cognitive function, appearance, or general well-being, discuss it with a licensed healthcare professional. They can help you evaluate approved, evidence-based options rather than relying on an unapproved or investigational compound. This calculator is intended only for transparent research-reference calculations and does not determine an appropriate amount, recommend use, or replace professional medical guidance.

About the author

Maria Hrabina is a pharmacist and scientific reviewer with a strong interest in peptide science, pharmacology, and emerging therapeutic compounds.

Her work focuses on understanding how peptide-based compounds interact with biological signaling pathways and how they are being investigated across areas such as metabolic health, dermatology, recovery, regenerative research, and pharmaceutical development.

Maria follows research on a broad range of peptides, from compounds used in approved medicines to experimental molecules still being evaluated in laboratory, preclinical, and clinical studies.

Her approach combines scientific curiosity with critical evaluation of evidence. She believes promising mechanisms and early research deserve attention, but should not be presented as established clinical benefits until they are supported by adequate human data.

Her areas of focus include scientific literature review, mechanisms of action, pharmacology, pharmacokinetics, safety, pharmaceutical formulation, and the overall quality of evidence behind peptide-based compounds.

She is particularly interested in the process of translating an experimental molecule into a reliable pharmaceutical product — including compound characterization, purity, stability, formulation, dose selection, safety assessment, and controlled clinical trials.

Maria believes peptide science has significant long-term potential, but that its progress depends on rigorous research, high manufacturing standards, transparent safety data, and responsible scientific communication.

Through her writing, she aims to help readers understand both sides of peptide research: what makes these compounds scientifically promising and what questions remain before their potential can be considered clinically established.

Areas of interest: Peptide Science · Therapeutic Peptides · Peptide Pharmacology · Metabolic Peptides · Cosmetic Peptides · Drug Development · Pharmacokinetics · Drug Safety · Pharmaceutical Formulation · Emerging Therapies · Evidence-Based Medicine

Important: This tool is for informational and research-reference purposes only. Not intended for human or veterinary use.
← All peptides